
Postoperative Angle Closure After Pars-Plana Vitrectomy in Pseudophakic Eye
This case involves a 71-year-old male patient who underwent pars-plana vitrectomy due to a retinal detachment in his left eye. The patient was already pseudophakic at the time of the surgery. Additionally, a YAG capsulotomy had already been performed.
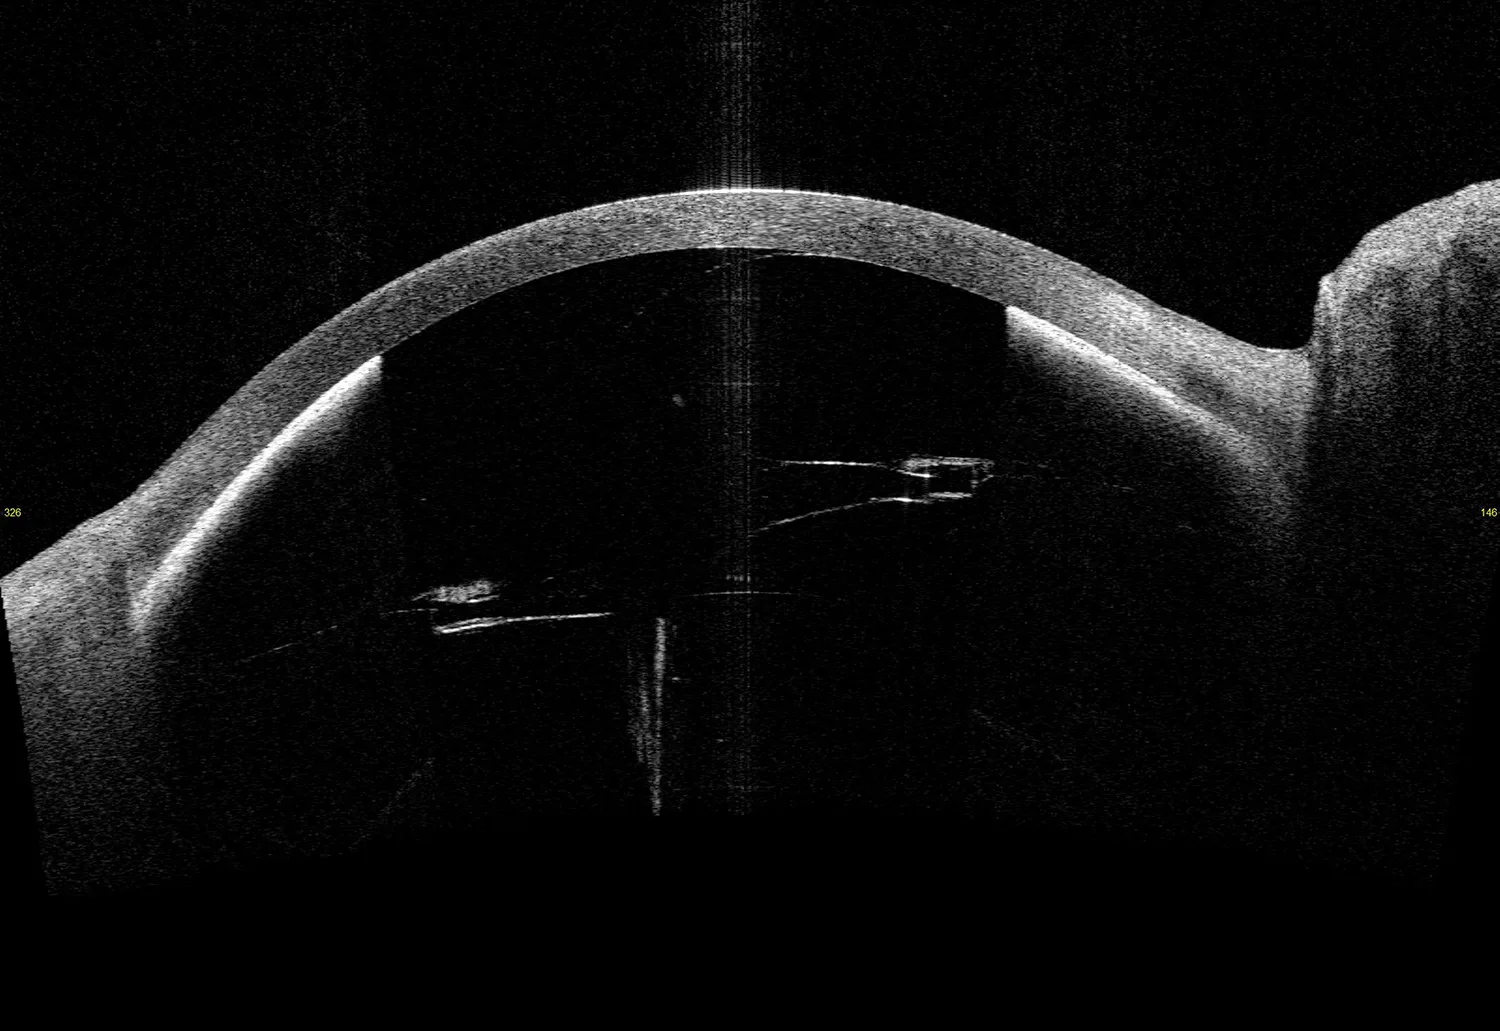
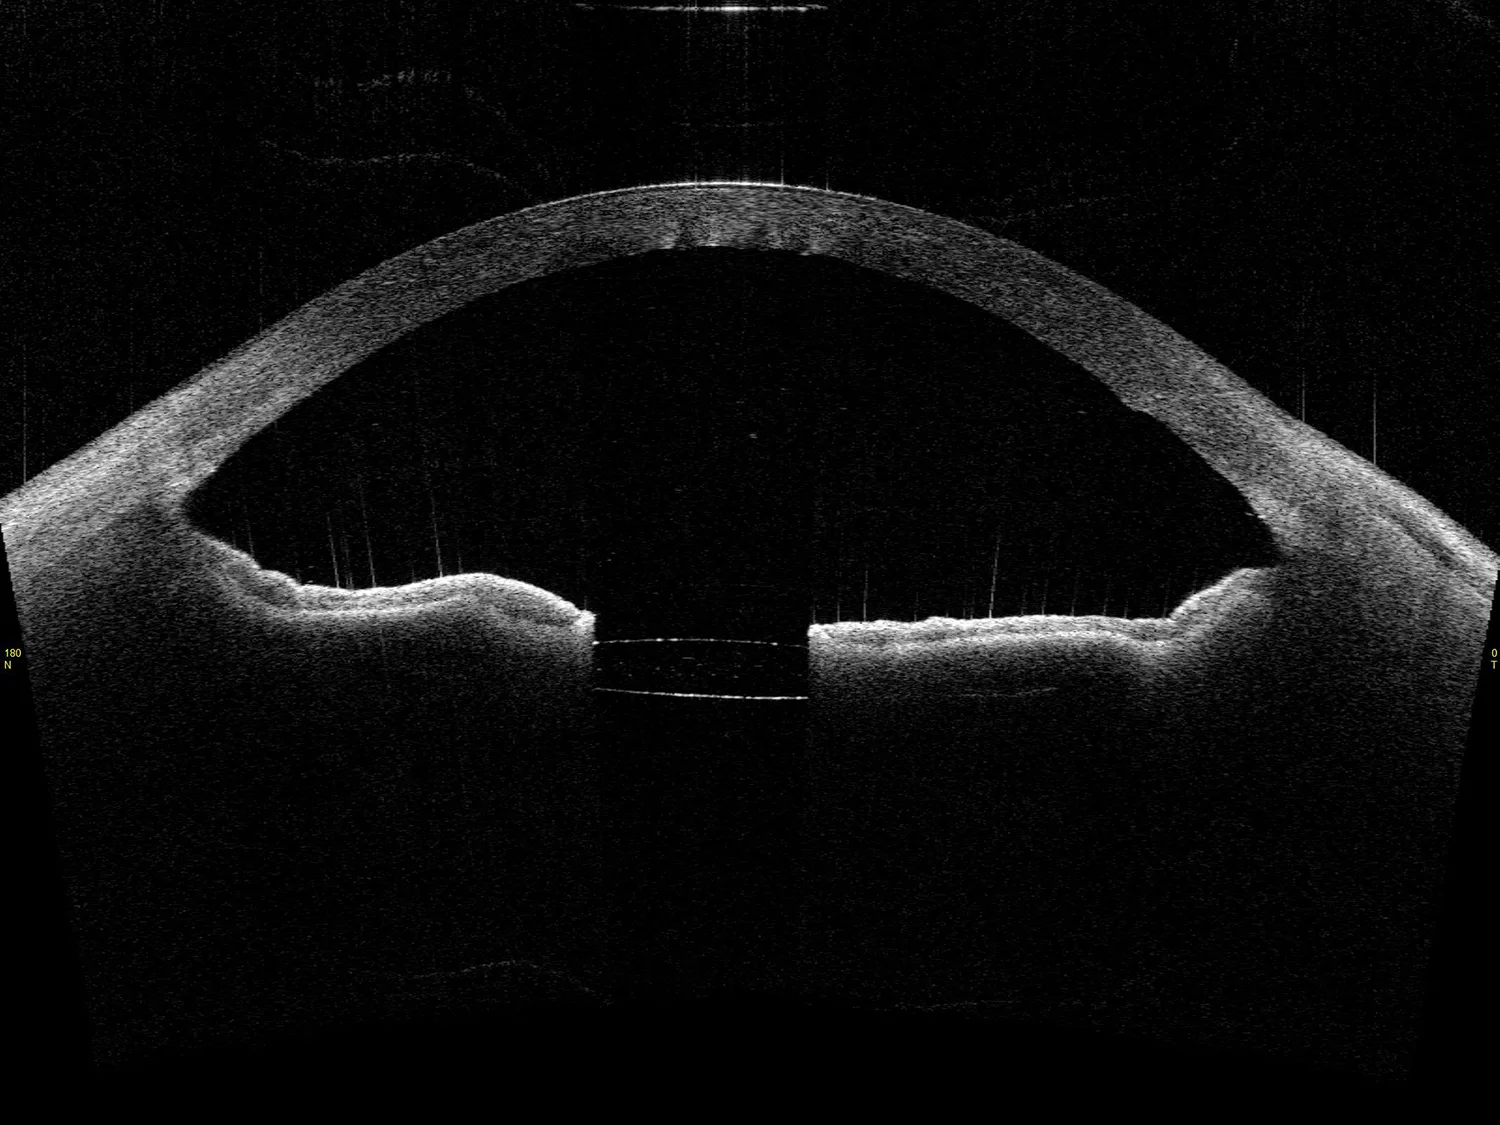
After an initially uneventful postoperative course, a complete angle closure developed on the second postoperative day due to a gas bubble in the posterior chamber, between the anterior IOL surface and the posterior iris, as a result of an absent capsular barrier. The intraocular pressure was 50 mmHg.
Subsequently, maximal local pressure-lowering therapy was administered, along with intravenous mannitol and acetazolamide. Furthermore the patient was instructed to adopt a prone position. Additionally, pilocarpine was applied to constrict the pupil.
The following day, the angle closure had resolved, and the gas bubble had shifted to the anterior chamber. The intraocular pressure was within the normal range at 11 mmHg.
This case illustrates the possibility of avoiding a potentially difficult surgery through sophisticated conservative methods.
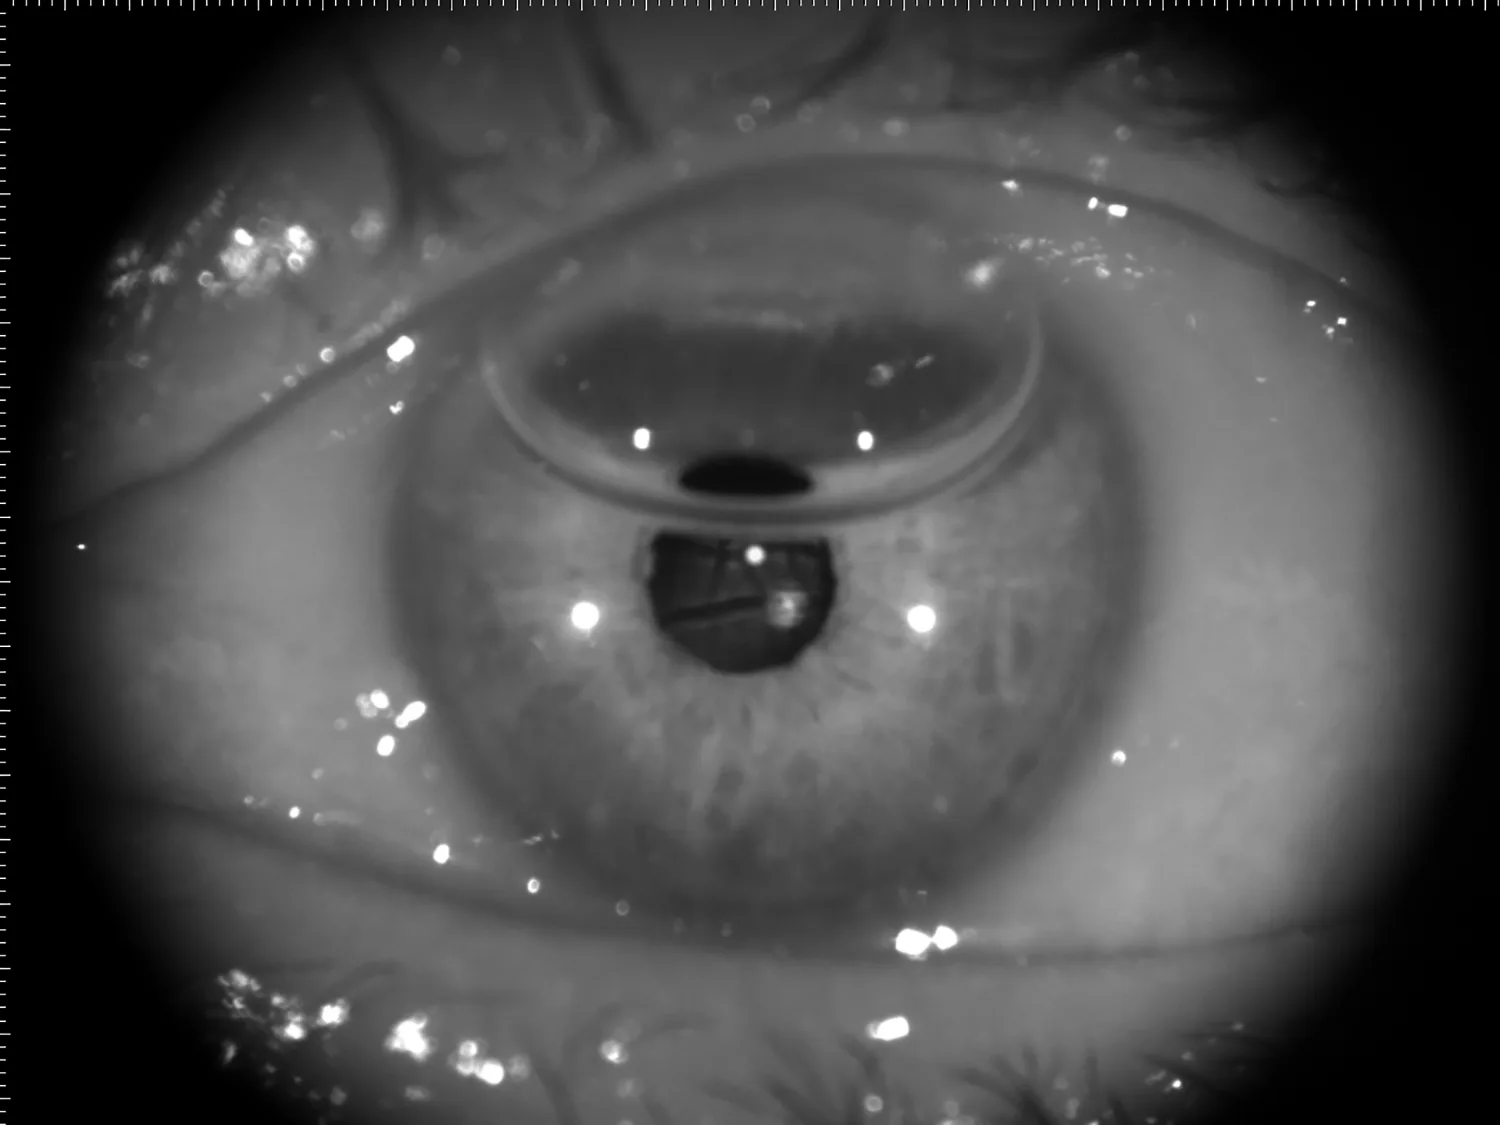
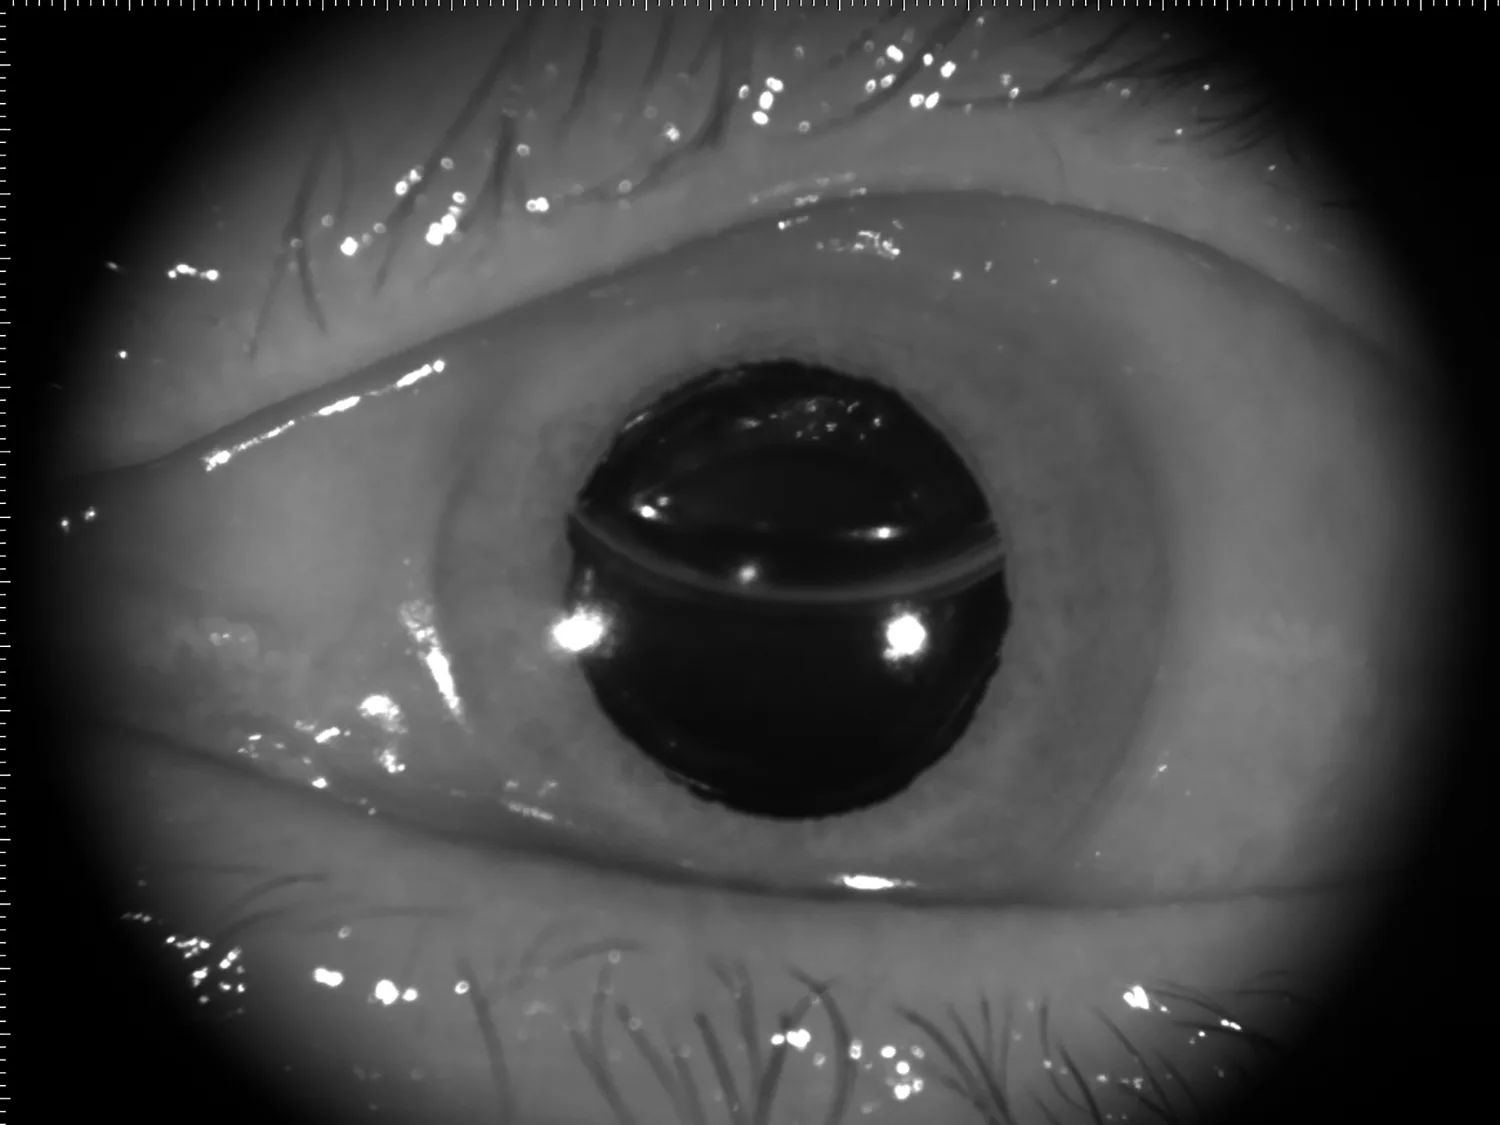
CASIA2 images of the left eye with the gas bubble in the posterior chamber leading to a 360° pupillary block
1 / 4
Further Questions?
Do you have any questions or require further information?
We would be pleased if you send us an inquiry.